What Is Sleep Anxiety?
Sleep anxiety is best described as the persistent worry or fear about falling asleep, staying asleep, or the consequences of not sleeping well. In essence, the mind becomes preoccupied with sleep itself—rather than simply experiencing occasional insomnia—and this preoccupation then interferes with the ability to rest. For example, you might lie in bed thinking: “What if I don’t fall asleep?”—and that thought alone triggers tension, physical arousal, and the very sleep difficulty you fear.
Some people may fear drifting off because they worry something will happen while they sleep, or that their lack of sleep will wreck their day. Because sleep anxiety feeds on itself, it often creates a vicious cycle: more worry leads to less sleep, which leads to more worry.
Why Sleep Anxiety Matters for Mental Health
Sleep is foundational to emotional regulation, cognitive function, and physical recovery. When sleep is compromised by anxiety, multiple domains of health suffer:
The Mind–Body Impact
Chronic sleep disturbance or fear around sleep activates the body’s stress systems—elevating cortisol, increasing sympathetic nervous system arousal, and reducing the restorative aspects of sleep (like deep NREM and REM cycles). Research shows sleep problems may precede or exacerbate anxiety disorders.
Daytime effects include poor concentration, mood-instability, irritability, and heightened sensitivity to stress.
Comorbid Mental Health Conditions
Depression
Reduced sleep quantity and quality is strongly linked to depression. Sleep anxiety may either emerge from depressed mood or contribute to it—low energy from poor sleep deepens hopelessness.
Anxiety Disorders & Generalized Anxiety
Sleep anxiety shares a core feature with generalized anxiety: intolerance of uncertainty. “What if I can’t sleep?” becomes a recurring worry. That worry itself fuels arousal and insomnia.
ADHD
Individuals with ADHD may struggle with hyperfocus, impulsivity, or poor sleep hygiene—making them more susceptible to worry about sleep and subsequent sleep anxiety.
OCD
Obsessive-compulsive patterns can show up around bedtime: repeated checking of clocks, re-reading alarms, intrusive thoughts about what may happen if you sleep.
BPD (Borderline Personality Disorder)
Emotional dysregulation, intense shifts in mood, and fear of abandonment or being uncontrolled can amplify night-time anxieties and interfere with sleep onset or maintenance.
Psychosis & Schizophrenia
Although rarer, some individuals with psychotic disorders may experience somatic or sleep-related delusions or fears (“If I fall asleep something bad will happen”). Sleep anxiety can be a complicating factor.
Eating Disorders
Body-image concerns, nutritional deficiencies, and high stress levels in eating disorders can increase night-time arousal, rumination, and sleep-related fear.
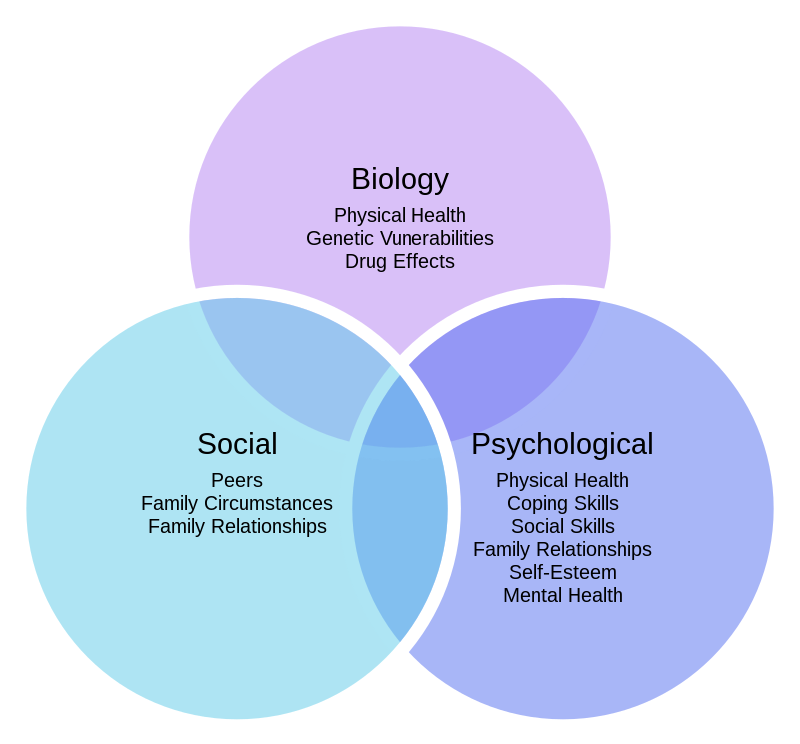
Because sleep anxiety intersects so many domains, an integrative approach (considering psychological, behavioral, and physical factors) is essential.
Recognizing the Signs and Symptoms of Sleep Anxiety
While occasional worry about sleep is normal—especially after a stressful day—sleep anxiety becomes clinically significant when it’s persistent, intrusive, and disruptive. Key indicators:
- Dread or nervousness when thinking about going to bed or falling asleep
- Racing thoughts or worry at the end of the day (“What if I don’t sleep?”)
- Physical sensation of tension, elevated heart rate, or restlessness at bedtime
- Difficulty initiating sleep (sleep onset latency >30 minutes regularly) or staying asleep
- Avoidance behaviors – staying up later, watching more TV, remaining on devices to delay sleep
- Reliance on sleep aids, caffeine, alcohol, or other substances to manage bedtime worry
- Daytime fatigue, poor concentration, irritability, emotional volatility
- Hyper-monitoring of sleep (hours slept, sleep tracker data) leading to stress about “not enough” or “bad” sleep
Some sources clearly define sleep anxiety as “worry or fear when it’s time to sleep” and note how it overlaps with but differs from insomnia: it is the fear of sleep more than the difficulty of sleep per se.
Causes & Underlying Mechanisms of Sleep Anxiety
Anticipatory Anxiety Around Sleep
One of the core mechanisms is anticipatory worry. Knowing you have to sleep, then worrying about failure to do it, sets off a chain of arousal. The body prepares for threat—not rest—and the result is difficulty relaxing into sleep.
Hyperarousal & Misinterpretation of Bodily Sensations
Sleep anxiety often involves heightened monitoring of bodily sensations (heart racing, muscle tension, temperature changes) and misinterpretation (“If my heart beats fast I won’t sleep”). This mirrors patterns seen in other anxiety disorders.
The Sleep–Anxiety Feedback Loop
Poor sleep increases anxiety and impaired emotion regulation, which then further disrupts sleep. This reciprocal relationship is well established.
Cognitive Distortions & Perfectionistic Worry
Beliefs such as “I must get 8 hours or I will be ruined tomorrow” or “If I don’t sleep now I’ll fail at everything tomorrow” drive the fear. Such “must‐sleeps” create pressure that undermines sleep.
Lifestyle & Behavioral Triggers
− Irregular sleep schedule
− High caffeine or stimulant intake late in day
− Excessive screen time or blue light exposure before bed
− Stressful work/relationship/home dynamics contributing to pre-bed worry
− Use of sleep-tracking devices that amplify worry about “quality” of sleep (orthosomnia)
Vulnerability from Co-Occurring Mental Health Conditions
Any condition that elevates baseline anxiety, disrupts sleep, or creates emotional dysregulation — such as depression, ADHD, BPD, psychosis or eating disorders — increases vulnerability to sleep anxiety.
Assessment and Diagnosis: When to Seek Help
While sleep anxiety is not officially a stand-alone diagnosis in the DSM-5, clinicians recognize it as a meaningful phenomenon connected with insomnia, anxiety disorders, and other mental-health conditions. Key features to assess:
- Duration and frequency: e.g., worry about sleep most nights for 1+ month
- Sleep metrics: how long to fall asleep, how often awaken, total sleep time
- Daytime consequences: fatigue, mood swings, cognitive impairment
- Behavioral patterns: checking devices, staying up later to delay sleep, over-monitoring
- Co-existing mental health conditions: depression, anxiety disorders, ADHD, OCD, eating disorders, BPD, psychosis
- Physical health factors: medications, caffeine, stimulants, medical sleep disorders (sleep apnea, restless legs, etc.)
Collaboration between primary care, sleep medicine, and mental-health providers ensures comprehensive evaluation and avoids missing other sleep disorders.
Evidence-Based Treatment and Management Strategies
Sleep Hygiene Foundations
- Consistent bedtime and wake time, including weekends
- Pre-bed routine that signals wind-down (no screens 30–60 min before bed)
- Comfortable sleep environment: dark, cool, quiet
- Limit caffeine/stimulants after early afternoon; limit alcohol
- Use bedroom only for sleep and intimate activity (not for work or worry)
Cognitive-Behavioral Approaches: CBT for Insomnia (CBT-I) + Sleep Anxiety
Cognitive behavioral therapy for insomnia is effective and widely used; it can be adapted for sleep anxiety by targeting worry about sleep, catastrophic beliefs, and bedtime arousal. Physicians or therapists may help challenge thoughts such as “If I don’t sleep now, I’ll fail tomorrow,” and replace them with balanced beliefs. Behavioral strategies include stimulus control (bed = sleep), sleep restriction (limiting time in bed to consolidated sleep), and relaxation training.
Anxiety-Focused Therapy
- CBT to address general anxiety, perfectionism, intolerance of uncertainty
- DBT (Dialectical Behavior Therapy) to help those with BPD or emotional dysregulation tolerate night-time uncertainty and bodily sensations
- ACT (Acceptance & Commitment Therapy) to reduce struggle against the sleep process and shift focus toward valued daytime actions
Mind-Body/Relaxation Techniques
Deep breathing, progressive muscle relaxation, guided imagery, yoga, and mindfulness all reduce physiological arousal and improve sleep onset. Harvard-based resources emphasize mind-body practice before bed.
Addressing Comorbid Conditions
- Depression/anxiety: Medication (SSRIs/SNRIs) may help reduce baseline arousal and negative mood.
- ADHD: Address stimulant use, evening hyperactivity, irregular routines.
- OCD/BPD/Eating Disorders: Integrated therapy to manage intrusive night thoughts, impulsivity, body checking or perfectionism that contribute to bedtime worry.
- Psychosis/Schizophrenia: Sleep routines and stress-management are part of relapse-prevention; fear about sleep may require specialized intervention.
Technology & Sleep Trackers: Use with Caution
While tracking sleep metrics can be helpful, obsessive monitoring (orthosomnia) may exacerbate sleep anxiety by turning sleep into performance again. Limit checking, focus on how you feel rather than just data.
When to Consider Medication or Professional Sleep Medicine
If sleep anxiety persists after behavioral/therapy intervention, or if other sleep disorders are present (sleep apnea, restless legs, narcolepsy), referral to sleep medicine is appropriate. Anxiety-reducing medications may be adjunctive, but ideally accompanied by behavioral work.
Prevention and Long-Term Maintenance
Develop a Balanced Mindset Toward Sleep
Recognize that one “bad” night of sleep is not catastrophic. Train the mind: “One night won’t ruin my day; I still have the next opportunity to recover.”
Build Emotional Resilience
Regular mindfulness, emotional check-ins, stress-management habits, and therapy help strengthen tolerance for uncertainty and bodily signals.
Maintain Regular Routines
Sleep, work, exercise, and leisure should have structured rhythms. Consistency breeds predictability and reduces bedtime worry.
Monitor Technology & Work-Life Boundaries
Avoid late-night screens or work encroaching into sleep time. Establish digital shutdown before bed.
Seek Social Support
Talking about your worry with trusted friends or a therapist normalises the experience and reduces shame. Peer or group interventions help.
Monitor Physical Health
Conditions like sleep apnea, restless legs, thyroid dysfunction, caffeine overuse, or medications may underlie or contribute to sleep anxiety. Coordinate with medical providers.
Clinical Case Illustration
Case Example:
A 28-year-old woman with long-standing generalized anxiety begins noticing racing thoughts as bedtime approaches: “If I don’t sleep I’ll mess up tomorrow,” she says. She starts staying up later to delay sleep and checking her sleep tracker frequently. She reports daytime fatigue, mood swings, and inability to focus at work.
Intervention: She begins CBT-I, replaces catastrophic sleep beliefs with realistic ones, practices nightly relaxation, shuts off her phone 60 minutes before bed, and limits checking sleep data. She also attends therapy for her anxiety disorder and addresses caffeine habits.
Outcome (4 months): Time to fall asleep reduces, morning mood improves, tracker checking drops. She feels empowered about her sleep instead of fearful of it.
Integrative Perspective: Why Sleep Anxiety Belongs in Integrative Psych Care
At Integrative Psych, we understand that sleep is not a luxury—it is a pillar of emotional and physical health. Sleep anxiety sits at the intersection of psychology, neurology, behavioral medicine and lifestyle.
We bring together:
- Psychiatric evaluation to identify or treat underlying anxiety, depression, ADHD or other conditions
- Psychotherapy (CBT-I, DBT, ACT) tailored to sleep anxiety and its mental-health overlaps
- Lifestyle medicine (nutrition, movement, circadian rhythm, sleep hygiene)
- Mind-body therapies to calm hyperarousal and improve nocturnal regulation
If you’re in the Chelsea, NYC area and struggling with fear around sleep, frequent nighttime worry, or waking feeling just as tired as when you went to bed—our team of clinicians is here to help you rebuild your relationship with sleep and reclaim restful nights.